Showing posts with label Behavioral Science Journal. Show all posts

Friday, 24 March 2023

Locus of Control and Vulnerability to Peer Pressure: a Study of Adolescent Behavior in Urban Ghanaian Context

 Abstract

Peer pressure is one thing that every individual is vulnerable to and has faced before at some point in their lives. It is becoming a serious health problem, especially for adolescents as well as concerned parents because, though not all peer pressure leads to health-related concerns or is negative, most are that need curbing, or treatment. Thus, NGOs, youth organizations, social welfare as well as parents, are looking for different ways to tackle this health-related issue in society. This research investigated locus of control on vulnerability to peer pressure in the African context. A survey was conducted using 144 adolescents from 2 Senior High Schools in Ghana with ages ranging from 15 to 19 years old. The following data collection instruments were used: Informed consent, Demographic data which used to group the students into categories based on age, class form and gender; the Nowicki-Strickland test (1973) and the Steinberg and Monahan resistance to peer influence scale (2007) measuring Locus of Control and Resistance to Peer Influence respectively. Statistical methods such as the independent t-test and Pearson Product Moment Correlation Coefficient (Pearson r) were used to study the relationships between age, locus of control, and resistance to pressure in the urban context. The findings revealed that there was no significant effect of locus of control on vulnerability to peer pressure, which still indicates that our study may be more bent towards the general idea that individuals with an internal locus of control are more likely to resist the pressure to conform by their peers.


Keywords: Adolescents; Locus of control; Peer Pressure; Health problems; Internal and External locus of control; Resistance

Read more about this article click on below link: 

https://lupinepublishers.com/psychology-behavioral-science-journal/fulltext/locus-of-control-and-vulnerability-to-peer-pressure-a-study-of-adolescent-behavior-in-urban-ghanaian-context.ID.000177.php

Read more Lupine Publishers Google Scholar articles 

https://scholar.google.com/citations?view_op=view_citation&hl=en&user=W3Gr-PEAAAAJ&cstart=20&pagesize=80&citation_for_view=W3Gr-PEAAAAJ:blknAaTinKkC

Tuesday, 15 November 2022

Children’s Fear From Dentists, Based on Literature Data

 Abstract

Introduction: Providing quality dental services, priority is given to patients’ approach to painless treatment at the dentist. The pain experienced by previous dental treatments, triggers the appearance of the feeling of fear that precedes the next dental intervention.

This picture becomes even more difficult when talking about pediatric age and the feeling of fear or anxiety experienced by this age before dental treatment. Fear of dentists has its origins in childhood, so logically, if fear and anxiety about dental interventions are to be analyzed, the age of study on this topic should be specifically pediatric age.

Materials and methods: The study is of review type based on the collected articles on the assessment of fear and anxiety in pediatric ages. A total of 14 articles and literature sources, which were collected based on the study selection criteria. The study was designed in the context of coping with data figures published by various articles on dental fear and anxiety in pediatric age specifically.

Results: Based on the data collected, 23% of children reported emotional distress in dealing with the dentist where only 12% of them expressed feelings of fear.64% of patients appreciate the way the doctor dresses, with white aprons giving him more confidence and not fear.70% of pediatric patients did not have the feeling of fear of wearing the mask during dental treatments. Feelings of fear, according to children, leave for a clinic decorated according to age.

Conclusions: Maintaining oral hygiene leads to a healthy dental status that does not face pain originating from the tooth, and consequently, not recognizing the pain reduces sensitivity and expectation to dental fear or anxiety. The visual appearance of the clinic and the doctor speaking with body language affects the expectation at the level of fear perception before dental treatment.

Read more about this article: https://lupinepublishers.com/psychology-behavioral-science-journal/fulltext/childrens-fear-from-dentists-based-on-literature-data.ID.000219.php

Read more about Lupine Publishers Google Scholar Articles: 

https://scholar.google.com/citations?view_op=view_citation&hl=en&user=W3Gr-PEAAAAJ&cstart=20&pagesize=80&citation_for_view=W3Gr-PEAAAAJ:maZDTaKrznsC

Friday, 29 July 2022

Employees’ Sense of Entitlement Toward Their Supervisors and its Association with Burnout and Job Satisfaction: Assessing A Multidimensional Construct

 There has been increased interest on the part of both organizations and the academy in the entitlement attitudes of employees. The vast majority of studies on employee entitlement have construed it as a unidimensional dispositional trait and have generally revealed strong correlations between sense of entitlement and negative workplace behaviors, suggesting significant implications for organizational outcomes. The goal of the current study was to develop and validate a self-report measure that views employees’ sense of relational entitlement toward their supervisors (SRE-es) as multifactorial. Findings indicated initial evidence of the validity of the SRE-es three-factor structure, reflecting employees’ adaptive (assertive) as well as pathological (restricted or exaggerated) attitudes regarding the assertion of their needs and rights toward their supervisors. Findings also indicated that an assertive sense of entitlement was linked with high job satisfaction and low burnout. Conversely, an exaggerated sense of entitlement was associated with high burnout and low job satisfaction. Restricted sense of entitlement revealed a mixed trend, being linked with both burnout and job satisfaction. The potential uses of the SRE-es scale are discussed.

Read more about article: https://lupinepublishers.com/psychology-behavioral-science-journal/fulltext/employees-sense-of-entitlement-toward-their-supervisors-and-its-association-with-burnout-and-job-satisfaction.ID.000220.php

Read more Lupine Publishers Google Scholar Articles: https://scholar.google.com/citations?view_op=view_citation&hl=en&user=W3Gr-PEAAAAJ&cstart=20&pagesize=80&citation_for_view=W3Gr-PEAAAAJ:M3NEmzRMIkIC

Friday, 10 December 2021

Lupine Publishers | Losses Loom Larger Than Gains: Neural Correlates Of Behavioral Gain-Loss Asymmetry

 Lupine Publishers | Scholarly Journal of Psychology and Behavioral Sciences

Introduction

Thomas Hobbes (1588-1679) proposed that voluntary behavior is governed by the principle of hedonism, that is, an individual’s sole intrinsic good is the overall pursuit of pleasure. A hedonist strives to maximize net pleasure by minimizing pain. Utility theory, which is a cornerstone of the rational perspective of economics, is rooted in the hedonist principle. However, the psychology of Homo economicus-a rational and self-interested individual with relatively stable preferences-has been challenged by numerous psychologists and behavioral economists. The purpose of our research was to explore the effects of small monetary gains and losses on choice behavior using a computerized game and to determine gain/loss ratio differences using both behavioral and electroencephalographic (EEG) measures.

A prominent example of gain-loss asymmetry is that losses loom larger than gains [1-4], meaning that the aversion to a loss of a certain magnitude is greater than the attraction to a gain of the same absolute magnitude. Such asymmetry is an indication that humans are sometimes biased in their decision making. Accordinng to Kahneman and Tversky [9], “The asymmetry of pain and pleasure is the ultimate justification of loss aversion in choice” [p. 157]. Kahneman, Knetsch, and Thaler [8] reported that “The existing evidence suggests that the ratio of the slopes of the value function in two domains, for small or moderate gains or losses of money, is about 2:1” [p. 199].

Rasmussen and Newland [14] reported a behavior-analytic experiment in which participants played a customized computer game that sometimes-produced reinforcers (gains) and sometimes punishers (losses) in the form of points exchangeable for money or, conversely, the loss of points and money. Their design included two alternating conditions. In one condition, a pair of reinforcement schedules were concurrently available. The ratio of reinforcer frequencies was adjusted systematically. The other condition consisted of the same pairs of reinforcement schedules, but a schedule of punishment was overlaid onto one of the reinforcement schedules. The authors reasoned that, in this way, they could measure the effect of punishers as the difference in the response ratios when punishers were delivered on one of the alternatives versus when punishers were absent from both alternatives. They concluded that the mean asymmetry ratio was approximately 3:1 (loss:gain) on average.

Kahneman [7] asserted that “the brain’s response to variations of probabilities is strikingly similar to the decision weights estimated from choices” [p. 315]. The electroencephalograph (EEG) may be used to record scalp visual-evoked potentials (VEPs), including event-related potentials (ERPs) [3,11]. Sokol-Hessner and Rutledge [15] reported that “Research on the neuroscientific basis of loss aversion has identified several critical neural components, suggesting a model of loss aversion in the human brain and providing links to the neuroscience of affect” [p. 315]. They reviewed several loss-aversion studies of young adults and adults and found that the means of loss aversion (computationally formalized as a multiplicative weight on losses relative to gains) in their model were between 1.3 and 2.5.

Kahneman and Tversky’s research method was cognitive. Rasmussen and Newland’s method was behavioral as was ours. However, we added an electrophysiological measure of the asymmetry of gains and losses. In the electrophysiological component of our study, the amplitudes of P300 waves elicited by gains and losses while playing the video game were measured in real time and converted to a gain/loss ratio. We hypothesized that the amplitudes of P300 waves recorded during a gain/loss behavioral procedure, when expressed as gain:loss ratios, would be directly related to their behavioral counterparts.

Method

Participants

The participants were 16 male undergraduate students enrolled at Brigham Young University (BYU), Provo, UT, USA 84602. They were recruited through an online recruitment platform following approval of our research protocol by the BYU Institutional Review Board.

Materials and procedures

We developed a computer game to produce behavioral data. Participants played the game in an experimental room, 9 ft by 9 ft, containing a table and chair. The table held a Dell® desktop computer (the game computer) equipped with a 17-in monitor and a mouse. The room was windowless and artificially illuminated. The computer had an Ethernet connection to a separate, identical computer that was in an adjacent room and that hosted the Emotive EPOC® Brainwear® software for recording the EEG and to monitor its functioning. The Emotive EPOC® device was placed on the participant’s head and contained 14 scalp electrodes. Written informed consent was obtained from all participants prior to the first experimental session. The participant was seated in front of the computer monitor and asked to read the instructions (written in English) for the game that appeared there. He was invited to play the video game in a series of 36-min sessions in which he could earn points on the screen. The net earnings were paid to the participant at the end of each session. In addition, the participants received a $50 bonus at the completion of the study. There were seven sessions. EEG recording was continuous during each session.

The SubSearch Game

Participants played SubSearch using the computer mouse to guide an underwater submarine and to retrieve as many yellow objects as possible before reaching the sea floor. When the cursor rested on the submarine, moving it moved the submarine. If the submarine was placed over a yellow object, clicking the mouse retrieved the object. Underwater barriers complicated the submarine’s movement between objects. Once the submarine descended to the sea floor, it was returned to the surface for a new descent, this time with more frequent barriers. Thus, the game became progressively more difficult as it continued. Only one panel was operative at a time. The other panel was darkened, and motion was paused. The game was played in two different vertical panels separated by a vertical line. Each panel was associated with its own interdependent concurrent variable-interval (inter conc VI VI) schedules of reinforcement. There was also a conjoint VI schedule of punishment during certain conditions on the left side of the screen. Unlike the traditional conc VI VI schedule in which the two schedules are independent of each other, the interdependent version assigned a reinforcer according to a preset probability generator. If, for example, the generator was set to assign twice as many reinforcers to the left panel than to the right panel (pL = 0.67), and the next reinforcer was assigned to the right panel, then it would be necessary for the participant to produce that reinforcer before the next one would be assigned. Thus, the interdependent schedule reduced the likelihood of extreme position (left or right) biases and assured that the scheduled proportion of reinforcers) between the two panels remained close to the proportion of those that were delivered.

After the participant clicked the “Start-OK” message on the screen, a 36-min session commenced. The game allowed the participant to move the cursor from one panel to the other. However, each switch produced a changeover delay of 2 s. During this interval, no reinforcers or punishers were delivered. Gains and losses were signaled by separate on-screen messages, each accompanied by a distinctive sound. For 0.5 s prior to the on-screen signal of a gain or of a loss, a fixation signal (a white + sign) was presented on the screen and followed in the same location by a message indicating either “Collect a coin to continue” for gains or “Insert a coin to continue” for losses. The gain-message appeared for 1 sec. Then the tab located at the bottom of the screen between the two counters began to blink. The game resumed after the participant clicked on the tab. Counters on each side of the tab displayed the net points for the respective side of the screen.

Each click during a session was coded, time stamped, and saved to an external MySQL database. The summary statistics included the total time spent responding in each panel, the total number of clicks that occurred in each panel, the total numbers of reinforcers and punishers that occurred in each panel, and the total number of changeovers. Each session consisted of a fixed sequence of six 6-min conditions (conditions 1-6). Three of them (1, 3, and 5) contained conc VI VI schedules of reinforcement only and three (2, 4, and 6) contained conc VI VI schedules of reinforcement and a conjoint VI schedule of punishment on the left side of the screen. Table 1 summarizes the scheduled frequencies of reinforcers and punishers in each condition. Condition 1 featured a conc VI60-s VI20-s schedule, meaning that 25% of the total reinforcers were allocated to the left panel and 75% to the right panel. There was no schedule of punishment. Condition 2 featured the same conc VI60-s VI-20 schedule of reinforcement plus a VI60-s schedule of punishments. In other words, 100% of the punishers were allocated to the left panel and no punishers to the right panel. The other four conditions featured different reinforcer ratios. Each unpunished condition was followed by a similar condition that included punishers only in the left panel under the same schedule as the reinforcers that were delivered in that panel. Each condition was accompanied by a different background color in each panels, for a total of six different colors. It should be noted that the values of the VI schedules in each concurrent pair of reinforcement schedules were selected to produce the same overall rate of reinforcement despite the difference in their ratios (1:3 in conditions 1 and 2, 1:1 in conditions 3 and 4, and 3:1 in conditions 5 and 6). The ratio of reinforcers to punishers was always 1:1.

Electrocortical activity

The head-mounted instrument was a wireless Bluetooth® Smart device (2.4GHz band) with 14 electrodes that transmitted at a sample rate of 128 Hz. It provided access to raw, densearray, high-quality EEG data with software subscription (EMOTIV Brainware®. The resolution was 14 bits with 1 LSB = 0.51 μV). The bandwidth was 0.2 -43Hz with digital notch filters at 50 Hz and 60 Hz. It included a digital 5th-order Sinc filter and a dynamic range (input referred) of 8400μV. It was AC coupled and powered by a lithium polymer battery (480 mV). The device sent the EEG data via a Bluetooth® connection to the computer to be recorded. In the game computer, certain in-game events, such as displaying a gain or a loss message on the monitor, triggered a signal to the second computer, it also compiled the data, temporally aligning the EEG data with the 8-bit codes received from the game and saved them to the hard disk. Because of the limitations of Bluetooth® range, both computers were in the same room, but the interface and the monitor for the second computer was in an adjacent room. The final output was a large csv file that contained a time-step column, the 14 electrode channels, and markers for each SubSearch on-screen message.

Event related potential analysis

VEPs are electrical potentials initiated by brief visual stimuli and are recorded from the scalp overlying the visual cortex. Amplitude (measured in μV) is defined as the difference between the mean pre-stimulus baseline voltage and specific voltages (positive and negative) measured within a time window. Latency (measured in ms) was defined as the time from stimulus onset to the point at which amplitude was measured within the window [11]. The ERP contains distinct waveforms that may be correlated with specific cognitive activities [2]. The labels N50, P100, N100, P200, N200, and P300 are commonly used, where P and N indicate positive or negative deflections, respectively, and the number indicates an ordinal position in the waveform. It should be noted that the P200, N200, and P300 are specifically ERPs; however, we used the term ERP to refer to all of the VEP components. Gehring and Willoughby [5] recorded brain activity coincident with monetary gains and losses and concluded that the amplitude was greater for losses than for gains. The ERP data were imported using EEGLab® with the ERPLab® add-on. EEGLab® is an interactive Matlab® toolbox for processing continuous and event-related EEG, magnetoencephalographic, and other electrophysiological data to produce independent component analysis, time/frequency analysis, artifact rejection, event-related statistics, and several modes of visualization of the averaged and single-trial data. A 1Hz high-pass filter, followed by a 50 Hz low-pass filter, was applied to the in-session recordings. Epochs were created for each gain or loss in the SubSearch game and ranged from 1,000 ms before the message appeared to 2,000 ms after it disappeared. Any epoch that contained an amplitude exceeding 150 mV was rejected. The epochs were averaged for gains and losses separately, resulting in a pair of summative waves (gain and loss) for each participant in each session. Then grand averages were created. The P300 component of the VEP was the focus of our analysis. The P300 wave was measured as the maximum positive deflection occurring between 250 msec and 500 msec following the presentation of brief visual stimulus. Yeung and Sanfey [17] found that, in studies of choice, the P300 can be influenced by several factors, including the magnitude of the chosen option, the valence and magnitude of the alternative option, and the relative value of the alternative outcome in comparison with the chosen outcome.


The data analysis consisted of signal filtering, amplifying, and averaging the EEG during the 1-s epoch immediately prior to the onset of a message on the monitor screen and during the 2-s epoch following the offset of the message. The analysis of the averaged ERPs focused on the previously indicated components of the average signal, with each component characterized by its amplitude, polarity (positive or negative), and latency. An ERP waveform consists of a series of peaks (here termed positive peaks) and troughs (negative peaks), but these voltage deflections reflect the sum of several relatively independent underlying, or latent, components. Isolating the latent components from the observable peaks and troughs of the waveform was challenging. The SubSearch game was designed to minimize latent components and to make sure that the evoked P300 was, as much as possible, a direct result of the experimental design. An important objective of the design was to separate the processes related to monetary gains and losses from possible confounding factors. The EEG does not only include ERPs but also other, “noisy” signals. The method we used to reduce the latter signals was signal averaging. All of the analyses featured epochs that were time-locked to the onset of the fixation signal that preceded the on-screen messages announcing reinforcers and punishers. Additionally, we examined the modulating effects of valence and magnitude on the ERP.


Figure 1 depicts the sequence of events in the computer game. Each ERP epoch began with a blank screen that appeared simultaneously with scheduled delivery of a reinforcer or punisher. Five- hundred ms later, a fixation mark appeared on the screen. After another 500 ms had passed, it disappeared, and the gain or loss message appeared on the screen. It marked the onset of the P300 waveform. Analysis of the epoch began 500 ms previous to the fixation signal. Immediately following the presentation of the reinforcer (or punisher) message, which remained on the screen until the participant resumed the game, there was a 1000-ms delay until the tab at the bottom of the screen between the two cumulative counters began to blink. During this interval, the game was inoperative and remained so until the participant clicked the tab.

Behavioral data analysis

Thorndike [16] formulated the basic principle of the law of effect, which stated that actions followed by feelings of satisfaction are more likely to be repeated, but actions followed by feelings of annoyance are less likely Herrnstein [6,13] produced systematic work on behavioral choice involving schedules of reinforcement. He found that, over time, the proportion of responses to an alternative matched the proportion of reinforcers received for responding to that alternative. If twice as many reinforcers were provided to one of two alternatives, then, on average, twice as many responses were directed to that alternative once response allocation was stable. Herrnstein summarized this regularity as follows and termed it the matching law of distributed (ongoing) choice between alternatives:

B refers to number of behavioral responses and R to the number of reinforcers that the responses produced. The two alternatives are designated by subscripts. This version of the matching law is actually a special case of the generalized matching law (GML; Baum, 1974):

that is, b = s= 1.0.

The parameters in this power function reflect a bias (b) for one source of reinforcement over the other and sensitivity (s) to changes in the distribution of reinforcers between the two sources, respectively. Under logarithmic transformation, the GML becomes a linear equation:

We used a procedure like that of Rasmussen and Newland and applied both the subtractive model as well as an indirect model to our results. The latter does not directly include punishers but, instead, represents the effect of punishers by variations in the effects of reinforcers. In other words, using this model, it is not necessary to include both reinforcers and punishers in the equation to measure their asymmetrical effect. All analyses were conducted using IBM SPSS Statistics 23 [13] and Microsoft Excel®. Measures included in the analyses were the number of responses (clicks) to the left and right alternatives (BL and BR) and the number of reinforcers provided by each (RL an d RR). The results were analyzed using equation 3. Asymmetry ratios were computed using antilogarithms of the bias estimates from the linear regressions for the conditions in which only reinforcers were used and those in which reinforcers and punishers were both used.

Results

Behavioral gain: loss asymmetry

Loss amplitudes were higher than gain amplitudes with an asymmetry ratio of 3.40. Table 2 contains the overall mean values of b for the No-punishers and With-punishers conditions, the 95% confidence intervals, and the asymmetry ratios for each session. Tables 3 and 4 contain the overall mean responses, obtained reinforcers, obtained punishers, and changeovers for the Nopunishers and With-Punishers conditions for the unpunished alternatives, respectively, for each of the participants. Table 5 is a summary of the overall estimated values of s and b in the Nopunishers and With-punishers conditions, and the asymmetry ratio for each participant.


Figure 2 displays the overall mean P300 waveform and other waveforms at electrode sites F3 (Panel B) and O1 (Panel C) for all participants according to the timeline. The approximate locations of the electrodes also appear. The reaction time (RT) was measured as the interval that began with the onset of the on-screen message and continued until the blinking tab was clicked. The mean RT was slightly shorter for the gain message (1512 ms) than for the loss message (1665 ms). In Figure 3, the overall mean amplitudes and standard errors are shown for each session: green bars for gains and red bars for losses. The blue lines represent the overall mean asymmetry ratio in each session. Five component waveforms appear, including the P300. The mean overall symmetry ratio for the P300 waveform was 1.99.

Correlation of the behavioral results with the electrophysiological results

Figure 4 displays the means of the asymmetry ratios derived from the two categories of data (behavioral on the x-axis and EEG on the y-axis) for each participant, together with the regression equation and R^2 (%VAC). Overall, the correlation coefficient was 0.852 and R^2 = 0.738.

Figure 4: Linear Regression of the Asymmetry Ratios for Each Participant Derived From the Behavioral Data (X-Axis) and From the EEG data (Y-Axis).


Discussion

Our results demonstrated a direct, robust correlation between behavioral and EEG measures of gain-loss asymmetry. The overall mean asymmetry ratio from our behavioral results was higher (M = 3.40) than that from the cognitive results previously cited [5,17] and from Rasmussen and Newland’s [14] behavioral study (M ≈ 3.0). For our EEG results, M = 1.99. One possible reason for the larger ratio from our behavioral results may be the use of the EMOTIV EPOC+® and the incumbency on participants to wear it throughout each session and, at the same time, to avoid unnecessary movements (which could have interrupted Bluetooth® interconnectivity or added noise to the EEG record). Notable aspects of the research method and data analysis included the use of the interdependent schedules of reinforcement, the inclusion of six different schedules within the same session, and the achievement of relative stability of participants’ performance within seven sessions [12,16], and that our participants were men, but there were 16 of them in our study and five in theirs. We, too, utilized a computer game as the behavioral task, though the on-screen presentation in our game was more complex than in theirs, as was the concatenation of six conditions within a session as opposed to their presentation of a single condition over consecutive sessions. Our use of interdependent VI VI schedules of reinforcement produced ratios of reinforcement consistently closer to the programmed ratios than in their study, where the disparity between programmed and actual ratios produced by conc VI VI schedules of reinforcement was substantial. Also, when a VI schedule of punishment was conjoined with the reinforcement schedule in their procedure, the scheduled rate of punishment was half that of the scheduled rate of reinforcement as opposed to being the same rate, as in our experiment. As with reinforcers, their results displayed a considerable disparity between the scheduled and actual rates of punishers.

Finally, our study included the measurement of EEG activity concurrent with participants’ distributed choice behavior. The temporal alignment of the EEG record with the record of behavior during the same SubSearch session was critical to demonstrating the correlation between the two sets of data. This requirement was fraught with unanticipated complications and required extensive revision and testing of the communication protocol between both computers (see the earlier description of the procedure) before it was sufficiently reliable for use in the research we reported. Perhaps the most noteworthy outcome of our study was the strength of the positive correlation between the behaviorally derived and EEGderived asymmetry ratios. Though no extant models account for that relationship, its demonstration invites further investigation. For the present, we have concluded that losses affect ongoing behavior in a distributed-choice procedure more intensely than gains do and that this differential effect may be quantified using the record of brain activity that occurs simultaneously with distributed choice behavior. It is as if the brain holds a mirror to externally observable behavior, or vice versa.

  Read More Lupine Publishers Psychology And Behavioral Sciences Journal Articles:

https://lupine-publishers-psychology-journal.blogspot.com//


Monday, 22 November 2021

Lupine Publishers | An Investigation of Turkish Specialist and Practitioner Doctors’ Empathy and Cognitive Flexibility Levels and Interpersonal Relationship Styles

 Lupine Publishers | Scholarly Journal Of Psychology And Behavioral Sciences


Introduction

The interlocked relationship between mind and body has increasingly resulted in modern medical practices’ use of biopsycho- social and patient-centered models that emphasize various psychological and environmental factors [1-3]. In particular, patientcentered approaches are characterized by a serious consideration of patients’ views, preferences, values, and economic resources [4]. In addition to positively affecting various medical outcomes and patient satisfaction levels, patient-centered approaches have been shown to reduce the use of healthcare services, diagnostic tests, prescription, referral, and hospitalization, along with total annual healthcare expenses [5,6]. Given that visiting a physician may in itself induce considerable worry and anxiety in patients [7], physicians’ interpersonal communication competencies and styles can directly influence patients’ self-expression by providing them with a sense of being listened to and understood, which in turn acts on several factors such as patients’ anxieties about their illness, hope for a cure, and adherence to the treatment [8]. In the treatment of somatic diseases, talking about disease perception reveals the therapeutic effect of talking [9]. In this regard, empathy refers to a “cognitive quality” that by its interpersonal nature involves a physician’s capacity to understand and communicate about patients’ experiences, anxieties, and viewpoints [10,11]. Empathy has been reported to reduce patients’ anxiety and stress levels and to considerably influence positive health outcomes [12]. More specifically, physicians’ empathy has been shown to be significantly associated with diabetes patients’ clinical outcomes and result in shorter periods of the common cold [13-16].

As these studies point to a concrete and measurable effect in the immune system induced by a positively experienced subjective feeling, they further substantiate the strong relationship between mind and body. Among the factors that have transformed the physician-patient relationship from Emanuel’s paternalistic model to a conciliatory model are the rising socioeconomic level with social development, medical technologies that improve the quality of life, the development of patients’ rights, patients’ greater knowledge of their rights, developments in the concept of seeking rights, physicians and patients putting more value on human rights, the widespread implementation of legal responsibilities and sanctions on physicians and patients, legal obligations, the application and dissemination of the understanding of quality in healthcare, rising health literacy, and the existence of complaint mechanisms through communication centers of public institutions [17]. Studies supporting patients’ empathy expectations in Turkey [18-23] as well as focusing on patient-physician communication show that empathy stands out as a very important element, sometimes alone and sometimes together with other variables [24-26].

There are many studies that evaluate empathy education and empathetic attitudes of students in the basic medical education process in medical schools and investigate how empathy can be developed [27-33]. As another significant variable of this study, cognitive flexibility is regarded as a form of fluid intelligence marked by the skill of providing alternative solutions to different situations [34]. This construct is closely related to the neuro-psychological concepts of role- and perspective-taking, which entail numerous cognitive flexibility dimensions such as understanding others, selecting appropriate behavior, thinking about and generating different ideas, possessing a repertoire for different responses, and exchanging ideas with others in decision-making [35]. Literature on cognitive flexibility related to personnel working in the healthcare field is quite limited. A study on nurses found that coping skills and flexibility were positively correlated with psychological adjustment [36]. A study of medical students and residents showed that incorporating cognitive flexibility and perspective-taking skill instruction has implications for reducing conflict and stress, as well as improving wellness levels [37]. Empirical studies demonstrate that increased cognitive flexibility is linked to reduced levels of experiencing social difficulties, stress, depression, anxiety, and rage [38-42]. Conversely, cognitive flexibility has been found to be related to positive personal outcomes such as critical thinking, selfesteem, social skills, self-competence, and coping with stress [43- 45].

Although limited amount of evidence exists in the literature, there are several empirical studies that substantiate the relationship between empathy and cognitive flexibility. In one major example, neurological patients with various etiologies and cerebral lesions were found to manifest significantly lower empathy than healthy normal adults. The same study found significant correlations, ranging from 0.5 to 0.6, between cognitive flexibility and empathy scores [46]. These data support the idea that cognitive thinking may be closely linked to empathic behavior either via granting a precognitive skill or by being part of another common basic process. The present study is designed to make comparisons between Turkish practitioner and specialist physicians in terms of empathy, cognitive flexibility, and interpersonal relations styles. In so doing, it tests the question of whether practitioners’ long-term interactions with their enrolled patients (i.e. spending more time with them, knowing them better) or specialists’ longer training histories are correlated with increased empathy and cognitive flexibility levels.

Methods

Participants

It is included family physicians, who have completed 6 years of medical training and specialists who have completed an additional 5 years. Family physicians see the patients registered with them and specialists see patients who can make an appointment anytime and anywhere. Inclusion criteria for data collection were determined as for specialists who work as clinician. Branches of specialists: 5 orthopedics, 8 chest diseases, 1 neurology, 4 obstetrics, 3 infectious diseases, 2 internal medicine, 1 physical therapy, 1 pediatric, 3 ENT, 2 urology. General practitioner work as clinician. Thus, the sample of the present study comprises 60 participants, i.e. 30 practitioners and 30 specialists. Demographically, 40% of the practitioners and 47% of the specialists were women. Additionally, 90% of the practitioners and 97% of the specialists were married. The age average for practitioners and specialists was 45.5 and 43.2, respectively. As mentioned above, participants’ working posts involved family health centers and state or training and research hospitals. Paper-and-pencil questionnaires were filled out by volunteer participants themselves in the major cities of Istanbul and Ankara between January and April 2019.

The questions that the study aims to measure in terms of the variables included are as follows:

Do long-term interaction and being familiar affect physicians’ interpersonal relationship styles?

Does residency training affect specialist’ relationship styles?

Assessment Instruments

To address its research questions, this research employed the Jefferson Scale of Physician Empathy, the Cognitive Flexibility Inventor, the Interpersonal Relationship Scale, and a sociodemographic form.

Jefferson scale of physician empathy

The Jefferson Scale of Physician Empathy (JSPE) is a 20-item, 7-point Likert-type scale. In a sample of medical doctors, its internal consistency was found to be around .80. In the Turkish context, this scale was adapted by Malkondu in 2006 and its validity-reliability study was done on a sample of dentists [47].

Cognitive flexibility inventory

Developed by Dennis and Vander, the Cognitive Flexibility Inventory involves 20 questions and two subscales entitled “alternatives” and “control” [28]. The alternatives subscale comprises 13 items that tap into the extent to which an individual is able to find alternative solutions to difficult conditions or can form alternative explanations for life situations and people’s behaviors. The control subscale is constituted by items that measure to what extent these predicaments can be controlled [48]. The Cronbach’s alpha values for alternatives and control subscale were reported as .91 and .84, respectively. Higher scores are indicative of increased cognitive flexibility [28]. Validity and reliability research for the scale’s Turkish version was undertaken, who found Cronbach’s alpha values of .90 for the whole scale, .89 for the alternatives subscale, and .85 for the control subscale.

Interpersonal relationship scale

Developed by this 31-item, 3-point Likert-type scale assesses individuals’ interaction styles with others. Two subscales measure nurturing and restraining styles, respectively. Nurturing relations involve skills such as expressing one’s needs in an open manner, treating the other person with a respectful and accepting style, and employing a constructivist discourse. Conversely, restraining communication styles are marked by behaviors such as selfrighteousness, condescension, short temper, verbal abuse, and mockery. The scale has been used in many studies and evidence has been obtained that it is valid and reliable [49-52] Subscales for nurturing styles, in turn, tap into open and respective styles, while the restraining styles subscale further comprises egocentric and condescending styles. The internal consistency coefficient for the whole scale was measured as .79. Cronbach’s alpha values for open, respectful, egocentric, and condescending styles were .73, .70, .56, and .78, respectively.

Results

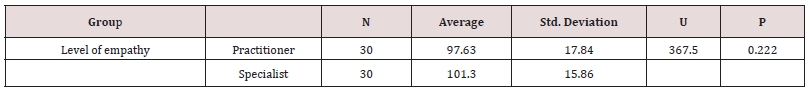
As reassessed from the data, the Cronbach’s alpha coefficient for the empathy scale turned out to be .847, while the cognitive flexibility subscales of control and alternatives had internal consistency values of .653 and .749, respectively. The interpersonal relationship subscales’ alpha coefficients ranged from 0.653 to 0.749. In terms of between-group comparisons, Mann-Whitney U tests indicated that, although specialists’ empathy level was higher than practitioners, the difference was not statistically significant. With respect to cognitive flexibility comparisons, Mann-Whitney U and t-tests substantiated that only the cognitive flexibilityalternatives subscale was significantly higher in specialists than practitioners. The associated values for these comparisons are shown in Tables 1,2. Interpersonal relationship style comparisons centered on nurturing (open-respectful) and restraining (ego centric-condescending) styles. As scores for open and egocentric styles were normally distributed for both groups, t-tests were employed for comparisons. Conversely, distributions for respectful and condescending styles were not normally distributed. Thus, the Mann-Whitney U test was preferred for comparisons in these domains. Accordingly, results indicated that specialists received significantly higher scores than practitioners in nurturing styles and significantly lower scores in restraining styles [Table 3].

Table 1: Comparison of empathy levels between specialists and practitioners.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

According to the Mann-Whitney U test, although specialists’ empathy levels were higher than practitioners’, this difference was not statistically significant, (p>0.05).

Table 2: Comparison of cognitive flexibility levels between specialists and practitioners.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

*p<0.05

According to the Mann-Whitney U and t-tests, alternatives subscale was the only statistically significant difference, and scores were higher for specialists, (p<0.05).

Table 3: Comparison of interpersonal relationship styles between practitioners and specialists.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

*p<0.05

According to Mann-Whitney U and t-tests, significant differences were found in terms of open, respectful, and condescending styles between practitioners and specialists. Specifically, specialists displayed higher open and respectful style scores and lower condescending style scores.

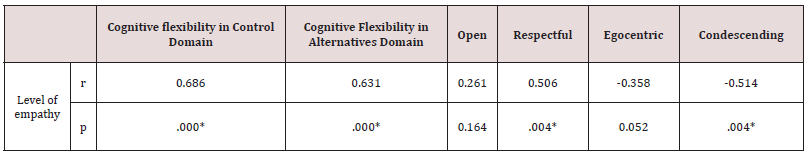
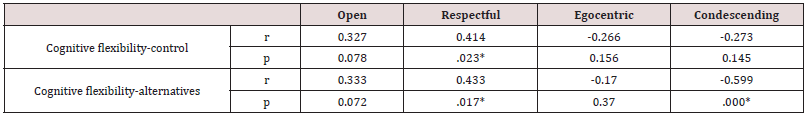
Spearman-Brown correlational analyses revealed a significant positive association between empathy and cognitive flexibility for practitioners. Similarly, for this group, the relationship between empathy and respectful relationship styles was also significantly positive, while the correlation between empathy and condescending styles was significantly negative [Table 4]. Specialists’ correlations between empathy and cognitive flexibility and relationship styles were not significant [Table 5]. Regarding correlations between cognitive flexibility and relationship styles, for practitioners, control and alternatives subscales were moderately associated with respectful styles. For specialists, cognitive and alternatives subscales were significantly related to open styles. For this group, an alternatives subscale was also moderately related to respectful styles. These significant positive associations are shown in Tables 6 and 7, respectively. Gender and marital status were not significantly related to specialists’ or practitioners’ empathy tendencies, relationship styles, cognitive flexibility total, or subscale scores. For practitioners, having longer careers contributed significantly to increased empathy, cognitive flexibility levels, and nurturing styles. For this group, age and cognitive flexibility was also positively related. For specialists, age and working duration were not significantly correlated with empathy levels, relationship styles, or cognitive flexibility levels. These results are shown in Table 8. According to the Spearman-Brown analysis, significant moderate associations were found between cognitive flexibility alternatives and respectful and condescending styles that were positive and negative in nature, respectively. There was also a positive moderate correlation between cognitive flexibility control and respectful style.

Table 4: Correlations between empathy and cognitive flexibility and empathy and interpersonal relationship styles in practitioners.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

*p<0.05

According to the Spearman-Brown analysis, positive significant correlations were found between empathy and cognitive flexibility control and alternatives subscales. Empathy was also positively related to respectful styles. The sizes of these relations were moderate. Another moderate correlation was found between empathy and condescending styles that was negative in nature.

Table 5: Correlations between empathy and cognitive flexibility and empathy and interpersonal relationship styles in specialists.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

Table 6: Correlation between cognitive flexibility and interpersonal relationship style in practitioners.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

*p<0.05

According to the Spearman-Brown analysis, significant moderate associations were found between cognitive flexibility alternatives and respectful and condescending styles that were positive and negative in nature, respectively. There was also a positive moderate correlation between cognitive flexibility control and respectful style.

Table 7: Correlation between cognitive flexibility and interpersonal relationship style in specialists.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

*p<0.05

According to Spearman-Brown correlation, the cognitive flexibility alternatives subscale was positively and moderately related to open and respectful styles. The cognitive flexibility-control subscale was positively correlated to open style.

Table 8: Associations between Empathy/Cognitive Flexibility and Age/Working Duration.

Lupinepublishers-openaccess-journals-psychology-behavioral-science

*p<0.05s

Discussion and Conclusion

Discussion

Findings revealed specialists’ empathy and cognitive flexibility scores were generally higher than practitioners’, yet the only statistically significant dimension was cognitive flexibilityalternatives in specialists.

In interpersonal relations, significant differences in terms of open, respectful, and condescending communication styles demonstrated that, compared to practitioners, specialist physicians were again more competent in these areas. These findings do not corroborate our tentative assumption when undertaking the study, namely that due to familiarity and longer interactions with their patients, practitioners should exhibit higher empathy, cognitive flexibility, and communication competence. Our particular pattern may have stemmed from various factors: First, with respect to cognitive flexibility, due to certain preexisting cognitive skills, individuals who become specialists may be predisposed to more competently assess alternatives in particular situations and problems. Indeed, [53] proposed that the predominant characteristic of experts is the ability to manipulate versatile mental representations, which in turn enables them to adapt better to environmental changes and use their knowledge more efficiently among different tasks. Alternatively, one may consider the effect of specialists’ education in terms of both different cognitive skills acquired and being exposed to courses on patient-doctor interactions. It is conceivable that different specialist branches, the cultures of hospitals and medical schools, socioeconomic status, or even cities of residence may play a role in augmenting or hindering cognitive flexibility, empathy, and interpersonal relationship style. In this regard, future studies may include these variables to determine both their unique and interactive effects for various professionals in the medical field.

Although not displaying a statistically significant difference, higher empathy levels and interpersonal relations competence of specialists may be linked to particular predicaments of the medical system in Turkey. In Turkey, practitioners regularly receive a burdensome number of registered patients. In this sense, it is reasonable to suggest that practitioners may have developed certain emotive strategies to mitigate the emotional burden that accompanies personal interactions with their patients. Alternatively, the mundane and repetitive tasks of referrals to specialists and renewing prescriptions may also hamper the tendency to develop a genuinely empathetic understanding of patients’ problems and emotional states. Conversely, specialists in Turkey accept additional patients in return for extra income, which offers them an opportunity to control the overburden they experience. These points highlight the importance of considering the significant role that the nature of healthcare systems may play in determining the quality of interpersonal communication and empathetic interaction. It is particularly telling that both specialist and practitioner empathy scores in Turkey are well below those reported by international studies, which lends support to the idea that predicaments in healthcare systems may greatly compromise cognitive flexibility and empathy. As compared to our scores of 101.30 for specialists and 97.63 for practitioners. Reported international physicians’ empathy levels in human-centered and technology-centered specialty fields as 112.9 and 106.9, respectively. Average physician empathy levels were found to be 120 in the United States [54-60].

In another major finding, in a practitioner sample within group analyses, the present study substantiated empathy’s significant relation to cognitive flexibility and interpersonal relations. These findings resonate with a prior study on Turkish university students [52] in which, as in this study too, empathy was found to be positively associated with open and respectful styles and negatively linked to condescending styles. Since in our study, empathy in specialists was not correlated to cognitive flexibility or communication style, one may consider the idea that, for specialists, the more intermittent and impersonal nature of doctor-patient interactions in the Turkish healthcare system enables the acquisition of satisfactory communication skills mainly via cognitive skills. Conversely, for health professionals such as practitioners and nurses who interact more closely with patients, communication skills may be induced mainly along the path of empathy.

Notwithstanding fields or branches among health professionals, the present study can be considered a noteworthy contribution to international research that investigates questions regarding empathy, cognitive skills, communication, and patient outcomes for healthcare professionals and workers at large. Indeed, a recent upsurge in international studies started to increasingly point to relations of these kinds. To give a few examples, prior research found a positive relationship between empathy and interpersonal relations in nursing students [61,62] and similarly posited positive relationships among empathy, perspective-taking, nurturing care, and friendly-harmonious relationship types in medical students [63]. Recently a strong relationship was suggested between empathic thinking and perspective-taking [64]. Hence, the present study lends support to the idea that the empathic and communicational skills of medical professionals should be one of the major avenues of research for promoting patient outcomes [65- 67].

This study offers ideas as to why training intervention is needed to improve communication and interpersonal relationships, and also includes suggestions about what the training program should cover. Some limitations should also be noted. The rather small sample sizes, including 30 participants for each group, and nonrandom, voluntary sampling procedures in this study should be considered caveats preventing satisfactory representativeness and generalizations around the globe. Additionally, variables such as doctors’ and patients’ personality traits and cultural and socioeconomic backgrounds were excluded from analyses. Lastly, our measuring instruments relied on self-report scales and are thus subject to biases rooted in the conveyance of subjective experience. These points should be taken into account by researchers while drawing cautious inferences for future research studies.

Conclusion

All in all, this study provides support to bio-psycho-social model patient-centered approaches and suggests their adoption positively influences patients’ psychological, mental, and physical health. Hence, the cultivation of an understanding recognizing the importance of interpersonal relations, communication skills, and interaction between the mind and body seems to be a worthwhile endeavor in the medical field. The long-term articulation of costeffective methods in healthcare systems – primarily training in factors promoting interpersonal relationships such as empathy and cognitive flexibility – would positively contribute to more efficient processes of diagnosis and therapy based on fulfilling interactions between physicians and patients.

 Read More Lupine Publishers Psychology And Behavioral Sciences Journal Articles:

https://lupine-publishers-psychology-journal.blogspot.com//


Locus of Control and Vulnerability to Peer Pressure: a Study of Adolescent Behavior in Urban Ghanaian Context

  Abstract Peer pressure is one thing that every individual is vulnerable to and has faced before at some point in their lives. It is beco...